
Rheumatoid Factor and Anti-CCP Positive: Does This Mean Rheumatoid Arthritis?
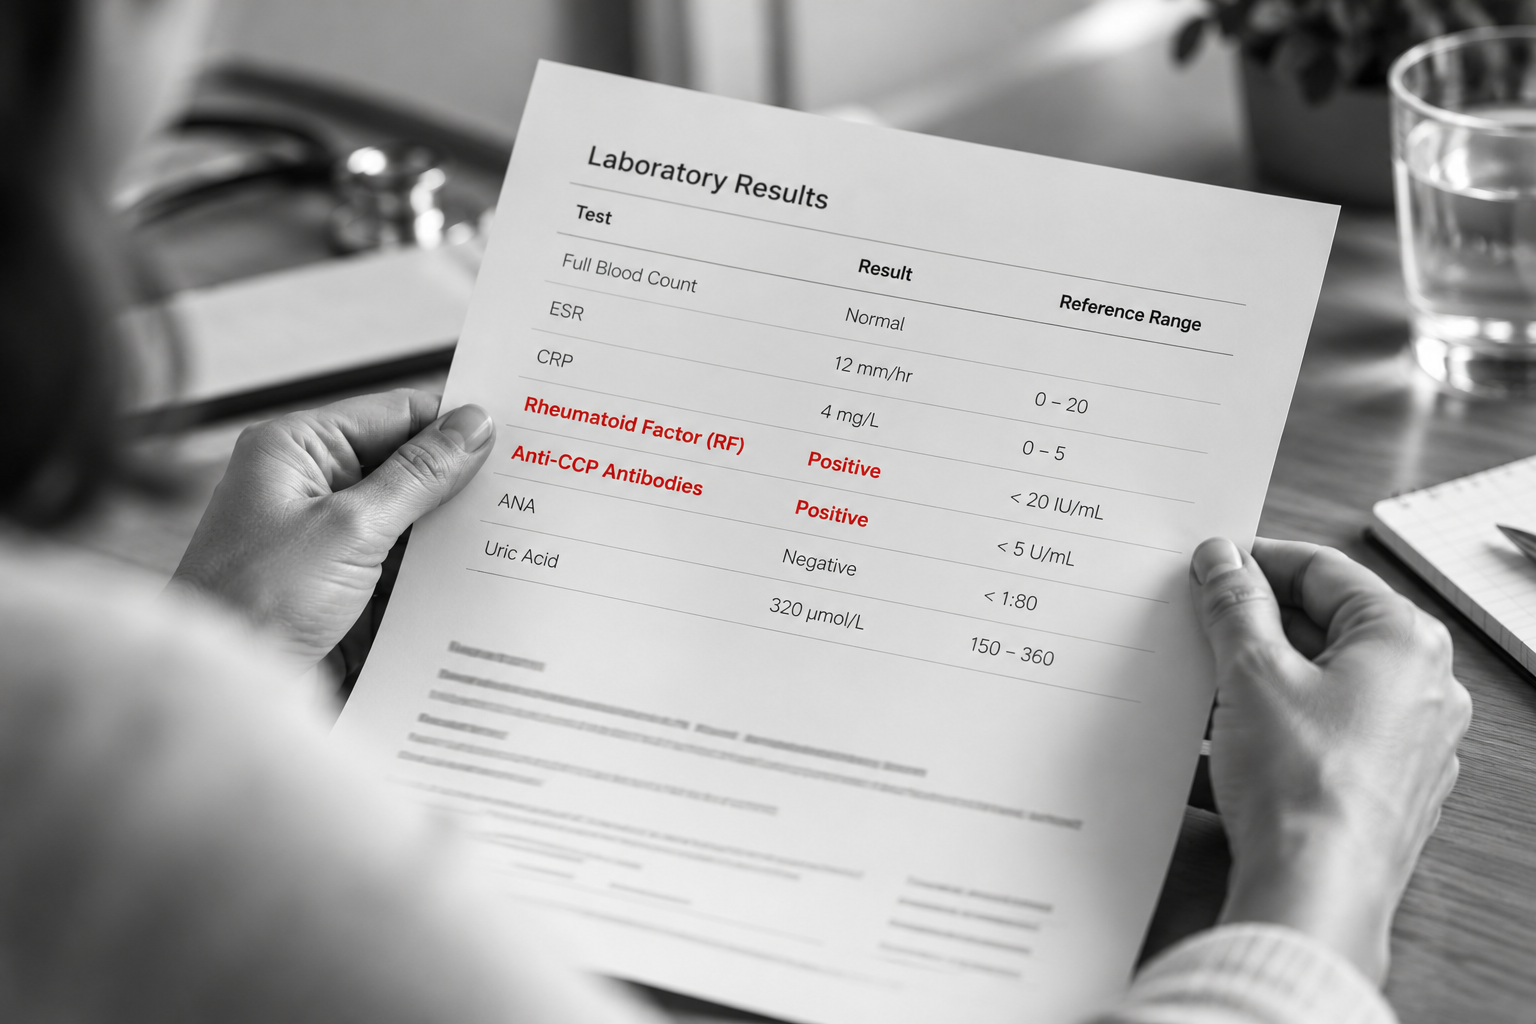
Blood tests are often an important part of investigating joint symptoms, but they can also cause unnecessary concern when the result is interpreted without the wider clinical context.
Two tests are particularly associated with rheumatoid arthritis: rheumatoid factor (RF) and anti-cyclic citrullinated peptide antibodies, usually shortened to anti-CCP. When either test is positive, it is understandable to assume that rheumatoid arthritis has been confirmed. In practice, the interpretation is more nuanced.
Rheumatoid arthritis is diagnosed by bringing together the pattern of symptoms, examination findings, blood tests and, where useful, imaging. Neither rheumatoid factor nor anti-CCP should be treated as a stand-alone diagnostic test. Some people with positive antibodies never develop rheumatoid arthritis, while others with clear inflammatory arthritis have negative antibody tests.
Understanding what these tests measure, how specific they are, and how they fit with the clinical picture helps avoid both overdiagnosis and missed diagnosis.
What is rheumatoid factor?
Rheumatoid factor is an autoantibody, which means it is an antibody directed against part of the body's own immune system.
Despite its name, rheumatoid factor is not unique to rheumatoid arthritis. It is found in many people with rheumatoid arthritis, particularly those with established disease, but it can also occur in other autoimmune diseases, some chronic infections and in a proportion of otherwise healthy people.
The likelihood of a positive result also increases with age.
For this reason, a rheumatoid factor that is only slightly above the laboratory reference range in someone with no inflammatory joint symptoms may have very different significance from a strongly positive result in someone with persistent swelling of the small joints of the hands and prolonged morning stiffness.
The test becomes useful when it is interpreted as part of a wider clinical assessment rather than treated as a diagnosis in itself.
What is anti-CCP?
Anti-CCP antibodies are directed against citrullinated proteins.
Citrullination is a normal biochemical process in which the amino acid arginine is converted into citrulline. In rheumatoid arthritis, the immune system can lose tolerance to some citrullinated proteins and begin producing antibodies against them.
The laboratory test detects antibodies against cyclic citrullinated peptides and is generally more specific for rheumatoid arthritis than rheumatoid factor.
In practical terms, this means that a positive anti-CCP result is less likely to be an incidental finding than a positive rheumatoid factor. However, greater specificity does not mean that the result should be interpreted without reference to symptoms and examination findings.
A positive anti-CCP result carries much more weight when there is evidence of inflammatory joint disease than when it is found incidentally in someone with no symptoms.
How are these tests used when rheumatoid arthritis is suspected?
The most important clinical finding in rheumatoid arthritis is usually persistent inflammatory synovitis.
Synovitis refers to inflammation of the lining of a joint. It can cause pain, stiffness, warmth and swelling, although the swelling may be subtle in early disease.
The pattern of joint involvement also matters. Rheumatoid arthritis commonly affects the small joints of the hands and feet, particularly the metacarpophalangeal joints at the knuckles, the proximal interphalangeal joints in the fingers and the wrists. Larger joints can also be involved.
Blood tests are then used to support the diagnosis.
Rheumatoid factor and anti-CCP are therefore most useful when there is already a clinical reason to suspect inflammatory arthritis. They are much less useful when ordered as broad screening tests in someone with non-specific pain and no evidence of joint inflammation.
What symptoms make rheumatoid arthritis more likely?
Rheumatoid arthritis usually causes a pattern of persistent inflammatory joint symptoms rather than isolated aches and pains.
Morning stiffness may last for a prolonged period, and symptoms can improve to some extent once the joints begin moving. Swelling can be persistent rather than intermittent, and several joints may be affected at the same time.
The distribution of symptoms also provides useful information. Symmetrical involvement of the hands and wrists can be suggestive, although rheumatoid arthritis does not always present in a textbook fashion.
It is also important to distinguish pain from inflammation. Osteoarthritis, tendon problems and mechanical joint pain can all cause significant symptoms without producing synovitis.
This is why examination remains so important. A blood test can suggest a possibility, but it cannot determine whether a joint is actually inflamed.
Does the level of rheumatoid factor matter?
The degree of positivity can influence how a result is interpreted.
A result that is only marginally above the reference range is not equivalent to a result that is several times the upper limit of normal. Higher levels are generally more supportive of rheumatoid arthritis when the clinical picture is compatible.
The 2010 ACR/EULAR classification criteria for rheumatoid arthritis distinguish between low-positive and high-positive rheumatoid factor or anti-CCP results, alongside the number and type of joints involved, inflammatory markers and the duration of symptoms.
These criteria are useful in research and clinical practice, but they are not simply a blood-test algorithm. They were designed for people in whom inflammatory synovitis is already suspected.
Laboratories may also use different assays and reference ranges, which is another reason why the absolute number should not be interpreted in isolation.
Is anti-CCP more specific than rheumatoid factor?
Anti-CCP is more specific for rheumatoid arthritis than rheumatoid factor and is therefore particularly useful when the diagnosis is uncertain.
It can also provide some prognostic information. People with established rheumatoid arthritis who are anti-CCP positive have, on average, a greater risk of developing erosive or radiographic joint damage than people who are anti-CCP negative.
That does not mean that an anti-CCP-positive patient will inevitably develop severe disease.
Modern treatment has changed the outlook for rheumatoid arthritis considerably. Early treatment using a treat-to-target approach can control inflammation, reduce symptoms and markedly lower the risk of progressive joint damage.
Anti-CCP should therefore be thought of as one piece of information about the disease rather than a prediction of an inevitable outcome.
Can anti-CCP be positive before rheumatoid arthritis develops?
Anti-CCP antibodies can sometimes be present before the first episode of clinically apparent rheumatoid arthritis.
This is scientifically important because rheumatoid arthritis often develops through a series of biological stages before persistent joint swelling becomes apparent. Autoantibodies may appear during this preclinical phase.
However, the presence of anti-CCP does not mean that rheumatoid arthritis is inevitable.
The probability of progression depends on several factors, including how strongly positive the antibody is, whether rheumatoid factor is also present, whether there are symptoms suggestive of evolving inflammatory arthritis, and other biological and environmental factors.
Someone with a positive anti-CCP result but no symptoms therefore requires a very different discussion from someone with the same result who has developed persistent small-joint stiffness and swelling.
What if both rheumatoid factor and anti-CCP are positive?
When both antibodies are present in someone with a compatible pattern of inflammatory joint disease, the likelihood of rheumatoid arthritis becomes considerably greater.
The combination is particularly persuasive when there is persistent synovitis, a typical joint distribution and other supportive findings such as raised inflammatory markers or inflammatory changes on imaging.
Even then, the antibodies remain part of the diagnostic picture rather than replacing it.
The same laboratory results found incidentally in a person with no joint symptoms need to be interpreted more cautiously.
This illustrates a broader principle in diagnostic medicine: the value of a test depends partly on the likelihood of disease before the test is performed. An abnormal result means more when there was already a strong clinical reason to suspect the disease.
What does seropositive rheumatoid arthritis mean?
Rheumatoid arthritis is sometimes described as seropositive or seronegative.
Seropositive rheumatoid arthritis usually means that rheumatoid factor, anti-CCP, or both are present.
Seronegative rheumatoid arthritis refers to rheumatoid arthritis in which these antibodies are absent.
The distinction can be useful, but it should not be overinterpreted. Seronegative rheumatoid arthritis can still produce clear inflammatory synovitis and clinically important disease.
Equally, antibody positivity without synovitis does not automatically establish rheumatoid arthritis.
This is why the clinical phenotype remains central even when sophisticated antibody testing is available.
Can rheumatoid arthritis occur with normal CRP and ESR?
Normal inflammatory markers do not exclude rheumatoid arthritis.
CRP and ESR measure systemic inflammation, but the degree of inflammation in the blood does not always mirror the amount of inflammation within individual joints.
Some people with early or relatively localised inflammatory arthritis can have normal CRP and ESR.
Conversely, raised inflammatory markers are not specific to rheumatoid arthritis and may occur with infection, other autoimmune diseases and many non-rheumatological conditions.
A person with persistent swollen joints therefore needs assessment even if CRP, ESR, rheumatoid factor and anti-CCP are all normal.
This is particularly important because early diagnosis and treatment can alter the long-term course of rheumatoid arthritis.
Why can rheumatoid factor be positive without rheumatoid arthritis?
Rheumatoid factor can appear in several settings outside rheumatoid arthritis.
It may be seen in other autoimmune conditions, including Sjögren’s syndrome and some connective tissue diseases. Chronic infection can also be associated with rheumatoid factor production, and low-level positivity becomes more common with advancing age.
For this reason, a positive rheumatoid factor found during broad health screening or while investigating unrelated symptoms should not automatically lead to a diagnosis of rheumatoid arthritis.
The result has to be interpreted against the background of the person’s symptoms, examination and other investigations.
Repeatedly measuring rheumatoid factor is usually less useful than understanding whether there is evidence of inflammatory joint disease.
What if rheumatoid factor is positive but anti-CCP is negative?
This is a common pattern and the meaning depends heavily on the clinical context.
If someone has convincing inflammatory synovitis, rheumatoid arthritis remains possible even when anti-CCP is negative.
If there is no evidence of inflammatory arthritis and rheumatoid factor is only mildly elevated, the result may be incidental or related to another condition.
The pattern over time can be informative. Persistent joint swelling, increasing morning stiffness or progressive loss of function would alter the significance of the result.
In uncertain cases, examination and imaging may be more helpful than simply repeating the same antibody test.
What if anti-CCP is positive but there are no swollen joints?
This situation deserves careful interpretation because anti-CCP is relatively specific for rheumatoid arthritis.
However, rheumatoid arthritis treatment is not normally started simply because an antibody is present in the absence of clinical arthritis.
The first question is whether there are symptoms that could represent an early inflammatory process. These may include persistent pain in the small joints, prolonged morning stiffness, difficulty making a fist, tenderness around the MCP joints or episodes of swelling that have not been present at the time of examination.
Some people with positive anti-CCP have no evidence of arthritis at all.
In this setting, the strength of the result, associated symptoms and whether rheumatoid factor is also present may help determine whether further follow-up or imaging is useful.
A specialist assessment can be helpful when the result is strongly positive or when symptoms are suggestive but the examination remains equivocal.
What is the role of ultrasound and MRI?
Clinical examination remains the starting point, but imaging can provide additional information when the diagnosis is uncertain.
Musculoskeletal ultrasound can detect synovial thickening, increased blood flow within inflamed synovium and erosive changes. It is particularly useful when there is concern about subtle inflammation that is difficult to confirm on examination.
MRI can detect synovitis, tenosynovitis, bone marrow oedema and early structural change, although it is not required in every patient.
Imaging should be used to answer a clinical question rather than simply because an antibody test is positive.
For example, ultrasound may be useful when someone has suggestive small-joint symptoms and positive anti-CCP but no obvious swelling on examination.
The interpretation still depends on putting the imaging together with the symptoms and blood results.
Why early diagnosis matters
Persistent uncontrolled inflammation in rheumatoid arthritis can lead to pain, loss of function and irreversible joint damage.
Modern treatment aims to identify active disease early and achieve remission or very low disease activity as quickly as possible.
This is why delaying referral because rheumatoid factor is negative can be problematic.
The opposite error also matters. Labelling someone with rheumatoid arthritis purely because a blood test is positive can lead to unnecessary anxiety, inappropriate treatment and a lifelong diagnostic label that may not be justified.
Accurate diagnosis requires both urgency where inflammatory arthritis is present and restraint where it is not.
When specialist assessment is useful
Rheumatology assessment is particularly helpful when there is uncertainty about how antibody results relate to symptoms.
This may include persistent joint swelling, prolonged morning stiffness, a strongly positive anti-CCP result, rheumatoid factor positivity accompanied by inflammatory-type symptoms, or abnormalities found during investigations performed for another reason.
A specialist assessment brings together the exact pattern and duration of symptoms, joint examination, antibody levels, inflammatory markers and any relevant imaging.
The outcome is not always rheumatoid arthritis.
Sometimes another inflammatory condition explains the symptoms. Sometimes the problem is mechanical rather than inflammatory. In other cases, the blood-test abnormality turns out not to represent active rheumatological disease.
That distinction is important because the purpose of assessment is not simply to confirm an abnormal test but to decide whether there is a disease that actually requires treatment.
The key message
Rheumatoid factor and anti-CCP are valuable blood tests, but neither should be interpreted in isolation.
Rheumatoid factor is less specific and may be positive in several conditions as well as in some healthy people. Anti-CCP is more strongly associated with rheumatoid arthritis, particularly when the result is clearly positive and there are compatible inflammatory joint symptoms.
Negative tests do not exclude rheumatoid arthritis when persistent synovitis is present, while positive tests do not establish the diagnosis in someone who has no evidence of inflammatory arthritis.
The most useful interpretation therefore comes from asking whether the blood-test result fits with the pattern of symptoms, examination findings, inflammatory markers and any imaging.
That approach allows rheumatoid arthritis to be identified promptly when it is present while avoiding unnecessary diagnostic labels when it is not.
Dr Animesh Singh, Consultant Rheumatologist. GMC: 6130215
Related Articles
Blood Tests in Rheumatology: What Do CRP, ESR, ANA and Rheumatoid Factor Really Mean?
Joint Stiffness and Swelling: When to suspect Inflammatory Arthritis?
Rheumatoid arthritis explained: symptoms, diagnosis and treatment.
Related Condition Pages
Please note, these posts are for general information only and do not constitute medical advice. Dr Singh would encourage you to speak to your healthcare professional to be assessed and managed for your specific symptoms.