Private Systemic Sclerosis / Scleroderma Specialist in London
Systemic sclerosis, sometimes called scleroderma, is an autoimmune connective tissue disease that can affect the skin, circulation, joints and internal organs.
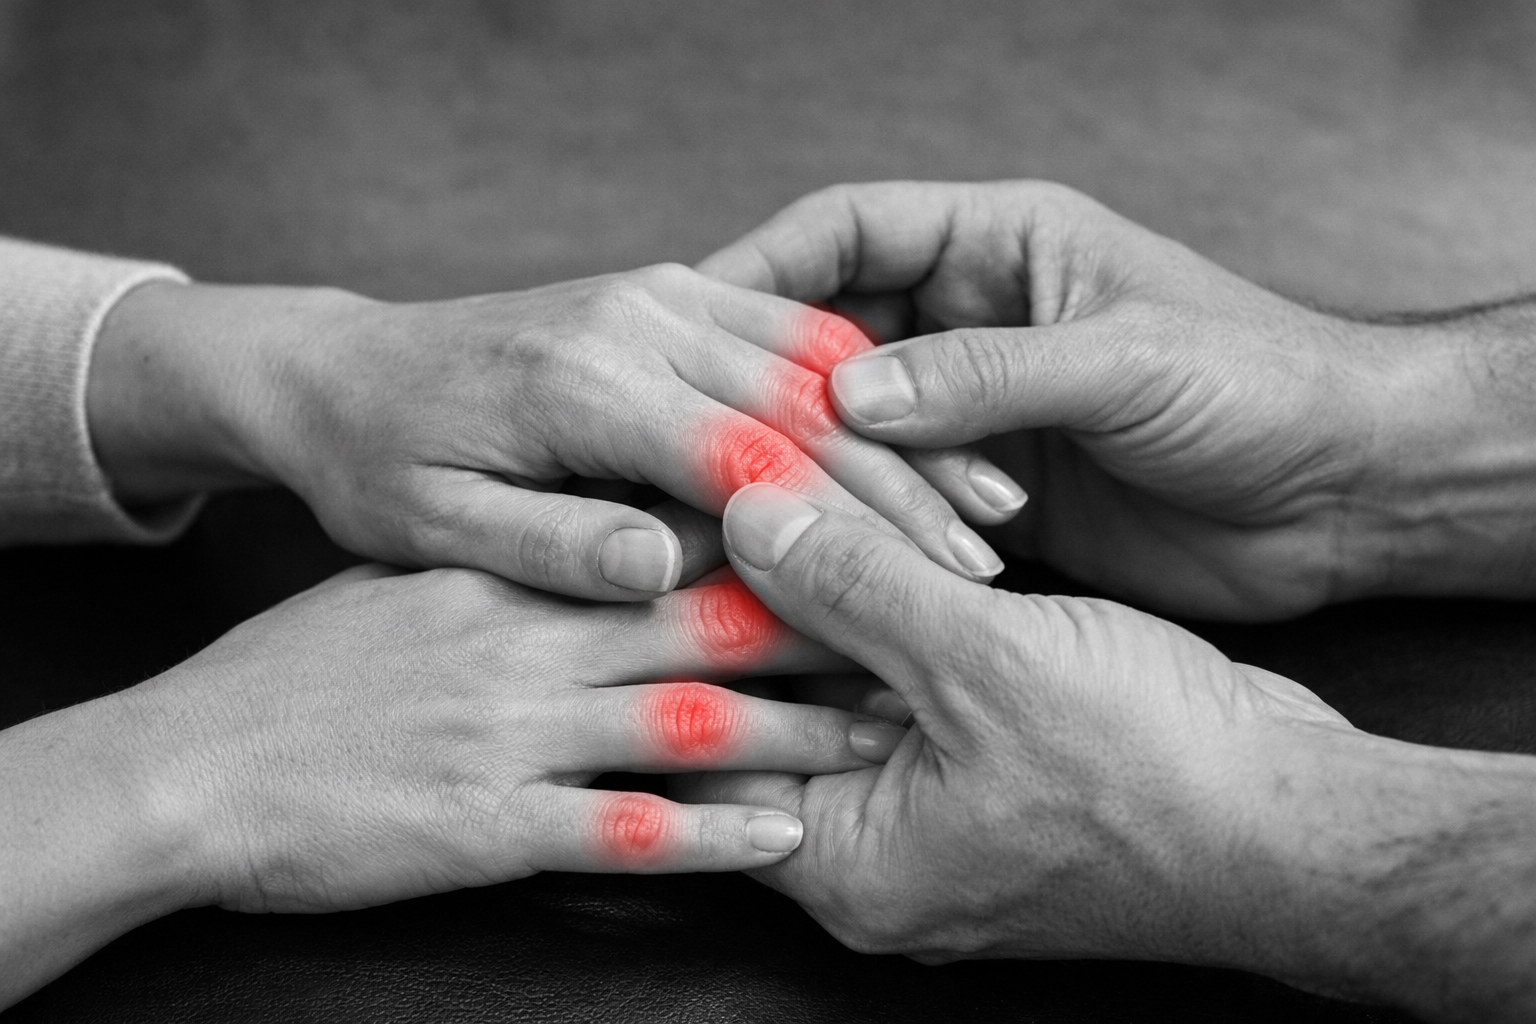
Raynaud’s phenomenon, puffy fingers, skin thickening, fingertip ulcers, reflux, swallowing symptoms or breathlessness may all be relevant when assessing possible systemic sclerosis.
Because symptoms can develop gradually and overlap with other conditions, specialist rheumatology assessment is important to understand whether symptoms are isolated or part of a wider autoimmune condition.
Dr Animesh Singh offers consultant-led assessment in London for patients with suspected systemic sclerosis, scleroderma, Raynaud’s phenomenon, abnormal autoimmune blood tests, skin changes or concern about connective tissue disease.
Private Systemic Sclerosis / Scleroderma Assessment at a Glance

Dr Animesh Singh is a Consultant Rheumatologist and General Internal Medicine Physician at the Royal Free Hospital, where he is Clinical Lead for Rheumatology. At the Royal Free, Dr Singh works in a specialist rheumatology environment where large numbers of patients with systemic sclerosis, Raynaud’s phenomenon and connective tissue disease are assessed.
He offers private assessment in London for patients with suspected systemic sclerosis, scleroderma, Raynaud’s phenomenon, abnormal autoimmune blood tests, skin thickening, puffy fingers, digital ulcers or concern about connective tissue disease. Systemic sclerosis can be complex because it may affect the skin, circulation, lungs, digestive system, joints and other organs. Specialist assessment helps identify the pattern of disease, decide what investigations are needed and develop an appropriate monitoring or treatment plan.
Dr Singh is highly rated by patients on Doctify and Google, with more than 800 patient reviews.

Recognising Possible Systemic Sclerosis Symptoms
Systemic sclerosis can affect different parts of the body, and symptoms may develop gradually.
Some patients first notice Raynaud’s phenomenon or puffy fingers, while others may have skin changes, reflux, swallowing symptoms or breathlessness.
🔹 Raynaud’s Phenomenon
Raynaud’s phenomenon is common in systemic sclerosis.
It may cause fingers or toes to change colour in response to cold or stress, with symptoms such as:
whiteness, blueness or redness
cold sensitivity
numbness or tingling
pain as circulation returns
🔹 Puffy Fingers and Skin Thickening
Systemic sclerosis can cause swelling, tightness or thickening of the skin.
Patients may notice:
puffy fingers
tight or shiny skin
difficulty removing rings
reduced flexibility of the fingers
🔹 Fingertip Ulcers or Pitting
Circulation problems may sometimes lead to fingertip changes.
These may include:
painful fingertip sores
slow-healing areas
small pits or scars at the fingertips
skin breakdown
These symptoms should be assessed carefully.
🔹 Reflux or Swallowing Symptoms
Systemic sclerosis can affect the digestive system.
Symptoms may include:
acid reflux
heartburn
difficulty swallowing
food feeling stuck
bloating or altered bowel symptoms
🔹 Breathlessness or Cough
Some patients develop lung involvement.
Symptoms may include:
breathlessness on exertion
persistent cough
reduced exercise tolerance
These symptoms may need further assessment, particularly if they are new or progressive.
🔹 Joint, Tendon and General Symptoms
Systemic sclerosis can be associated with musculoskeletal and general symptoms, including:
joint pain
stiffness
tendon discomfort
fatigue
reduced hand function
A rheumatology assessment can help determine whether these symptoms fit systemic sclerosis or another autoimmune rheumatic condition.
Understanding Systemic Sclerosis / Scleroderma
Systemic sclerosis is a connective tissue disease that can affect the skin, circulation and internal organs.
It varies significantly between patients, which is why careful assessment and appropriate monitoring are important.
-
What Is Systemic Sclerosis?
Systemic sclerosis is an autoimmune connective tissue disease.
It can cause inflammation, changes in small blood vessels and increased tissue thickening or fibrosis.
The condition may affect the skin, circulation, digestive system, lungs, heart, kidneys, joints and tendons.
-
Is Systemic Sclerosis the Same as Scleroderma?
The terms are closely related.
“Scleroderma” means hard skin and is often used by patients and clinicians to describe the condition.
“Systemic sclerosis” is the more precise medical term when the disease can affect the wider body, not just the skin.
-
What Is Limited Systemic Sclerosis?
Limited systemic sclerosis usually involves skin changes affecting areas such as the fingers, hands, face, forearms or lower legs.
It may be associated with Raynaud’s phenomenon and can involve internal organs, particularly the lungs, circulation and digestive system.
-
What Is Diffuse Systemic Sclerosis?
Diffuse systemic sclerosis usually involves more widespread skin thickening and may develop more quickly.
It can be associated with a higher risk of internal organ involvement, so careful assessment and monitoring are important.
-
Why Does Raynaud’s Matter?
Raynaud’s phenomenon is often one of the earliest symptoms of systemic sclerosis.
Most people with Raynaud’s do not have systemic sclerosis, but Raynaud’s that starts in adulthood, becomes severe or occurs with abnormal antibodies, puffy fingers, skin thickening or fingertip ulcers may need specialist assessment.
-
Can Systemic Sclerosis Affect Internal Organs?
Yes.
Systemic sclerosis can sometimes affect internal organs, including the lungs, heart, digestive system and kidneys.
The aim of specialist assessment is to identify whether there are signs of organ involvement and decide what monitoring or treatment may be needed.
How Systemic Sclerosis Is Assessed
Assessment of systemic sclerosis involves understanding the full clinical pattern, not relying on a single blood test.
A specialist rheumatology assessment brings together symptoms, examination findings, autoimmune blood tests and screening for organ involvement where appropriate.
-
The consultation explores:
when symptoms started
Raynaud’s symptoms and circulation changes
skin thickening or puffy fingers
fingertip ulcers or pitting
reflux or swallowing symptoms
breathlessness or cough
joint, tendon or muscle symptoms
previous autoimmune blood test results
-
Examination may include assessment of:
skin thickening
hand and finger movement
fingertip changes
nailfold area
joints and tendons
circulation
signs suggesting internal organ involvement
-
Blood tests may help identify patterns associated with systemic sclerosis and related connective tissue diseases.
These may include:
ANA
ENA antibodies
systemic sclerosis-associated antibodies
inflammatory markers
full blood count
kidney function
urine testing where appropriate
Blood test results must be interpreted alongside symptoms and examination findings.
-
The small blood vessels near the fingernails can sometimes provide useful clues.
Nailfold assessment may help identify changes seen in some connective tissue diseases, particularly systemic sclerosis.
Further vascular assessment may be considered if there are severe Raynaud’s symptoms, ulcers or circulation concerns.
-
Depending on symptoms and clinical findings, further assessment may include tests to check for internal organ involvement.
This may include consideration of:
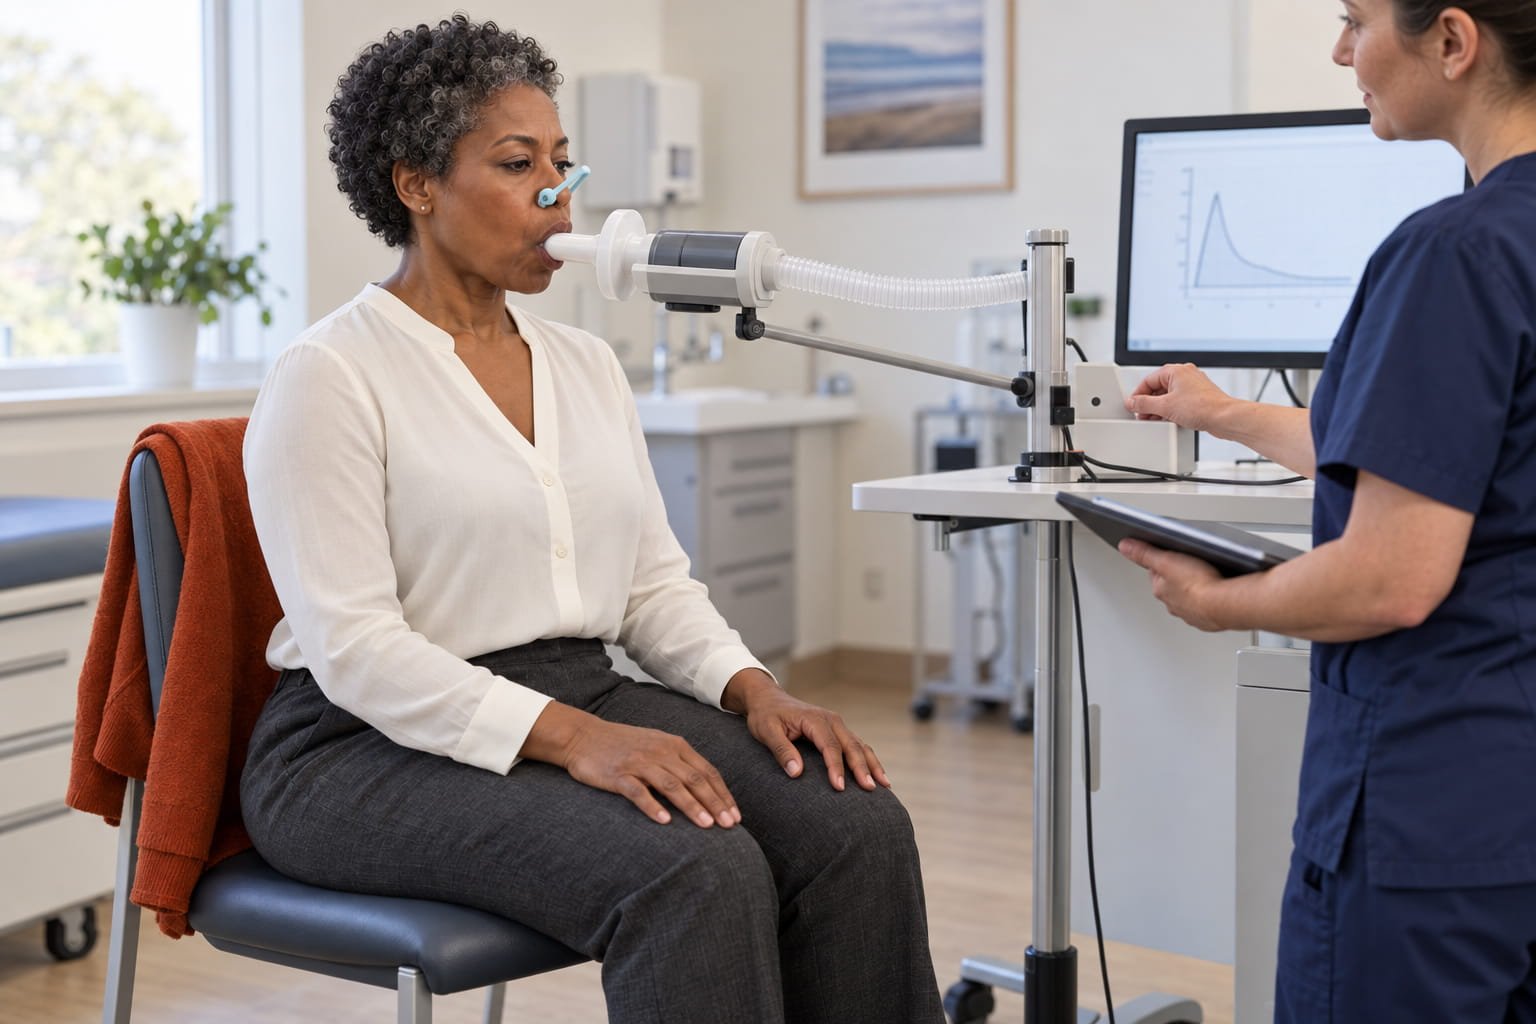
lung function testing
chest imaging
echocardiography
blood pressure monitoring
kidney and urine assessment
gastrointestinal assessment where relevant
The exact investigations depend on the individual clinical picture.
-
After assessment, patients are given a clear explanation of whether symptoms are consistent with systemic sclerosis, another connective tissue disease or an alternative diagnosis.
The plan may include monitoring, treatment, further investigations or coordination with other specialists where needed.
Treatment and Monitoring Options for Systemic Sclerosis
Treatment for systemic sclerosis depends on the pattern of symptoms, organs involved and severity of disease.
There is no single treatment approach that is right for every patient. Management is personalised and may involve symptom control, monitoring for organ involvement and specialist treatment where appropriate.
-
Raynaud’s symptoms are often managed with practical measures such as cold protection, trigger avoidance and smoking cessation.
Medication may be considered if symptoms are frequent, painful or complicated.
Treatment options may include calcium channel blockers such as nifedipine or amlodipine.
In selected patients with more severe Raynaud’s, digital ulcers or threatened tissue damage, medicines such as sildenafil, tadalafil or specialist treatments such as iloprost may be considered.
-
Systemic sclerosis can affect the skin, joints and tendons.
Management may include:
hand exercises and maintaining mobility
treatment of pain and stiffness
skin care
assessment of tendon or joint inflammation
occupational therapy or hand therapy where appropriate
If there is evidence of active inflammatory skin or musculoskeletal disease, treatment may include immunosuppressive medication depending on the clinical pattern.
Examples may include methotrexate or mycophenolate, selected according to symptoms, disease severity and individual patient factors.
-
Digestive symptoms are common in systemic sclerosis and may need active management.
Treatment may include:
reflux medication
dietary and lifestyle measures
swallowing assessment where needed
further gastrointestinal investigations in selected patients
Persistent reflux or swallowing symptoms should be reviewed because they can affect quality of life and may require specific treatment.
-
Some patients with systemic sclerosis develop lung involvement, including interstitial lung disease or pulmonary fibrosis.
Assessment and monitoring may include:
lung function tests
chest imaging where appropriate
oxygen levels or exercise assessment
respiratory specialist input
Treatment depends on the pattern and severity of lung involvement.
In selected patients, treatments such as mycophenolate, rituximab, tocilizumab or nintedanib may be considered, usually alongside specialist respiratory and rheumatology input.
-
Systemic sclerosis can sometimes affect the heart, kidneys and blood vessels.
Monitoring may include:
blood pressure checks
kidney function tests
urine testing
echocardiography
assessment for pulmonary hypertension where appropriate
Early recognition of complications is important because treatment depends on the specific organ involved.
-
Some patients require immunosuppressive or biologic treatment, particularly where there is active skin, lung, muscle or inflammatory organ involvement.
Depending on the clinical situation, options may include:
methotrexate
mycophenolate
rituximab
tocilizumab
other specialist treatments where appropriate
These treatments are not suitable for every patient. The decision depends on the pattern of systemic sclerosis, severity, antibody profile, organ involvement, previous treatments and potential risks.
-
Systemic sclerosis often requires collaboration between specialties.
Dr Singh works closely with specialist colleagues who are experienced in assessing and managing systemic sclerosis and its complications, including:
respiratory physicians
cardiologists
renal physicians
dermatologists
gastroenterologists
vascular specialists where appropriate
This multidisciplinary approach is important because systemic sclerosis can affect several organ systems, and treatment decisions often require coordinated specialist input.
Key Message
Systemic sclerosis treatment is personalised. Some patients mainly need monitoring and symptom control, while others require immunosuppression, biologic treatment or specialist organ-based care.
The right plan depends on the disease pattern, organ involvement, severity and individual patient priorities.
Concerned About Systemic Sclerosis, Scleroderma or Raynaud’s?
If you have Raynaud’s phenomenon, puffy fingers, skin thickening, fingertip ulcers, abnormal autoimmune blood tests or symptoms that may suggest systemic sclerosis, a specialist rheumatology assessment can help clarify the diagnosis and guide the next steps.
Dr Singh offers consultant-led assessment for suspected systemic sclerosis, scleroderma, Raynaud’s phenomenon and connective tissue disease, including advice on investigations, monitoring and treatment options.
When to Consider a Private Systemic Sclerosis / Scleroderma Appointment
A private rheumatology assessment may be helpful if you:
Have Raynaud’s phenomenon that started in adulthood
Have Raynaud’s with puffy fingers, skin thickening or tight skin
Have fingertip ulcers, pitting or slow-healing sores
Have a positive ANA, ENA or systemic sclerosis-related antibody
Have reflux, swallowing symptoms or unexplained digestive symptoms alongside Raynaud’s
Have breathlessness, cough or reduced exercise tolerance
Have joint pain, tendon symptoms or reduced hand function
Have been told you may have systemic sclerosis or scleroderma but remain uncertain about the diagnosis
Need advice about investigations, monitoring or treatment options
Would like a second opinion about symptoms, blood tests or previous assessments
Systemic sclerosis can vary significantly between patients. Specialist assessment helps determine whether symptoms fit systemic sclerosis, another connective tissue disease or a different explanation.

Systemic sclerosis can be difficult to diagnose and manage because symptoms may involve the circulation, skin, joints, digestive system, lungs and other organs.
Patients may seek a private rheumatology assessment for:
clarification of whether symptoms fit systemic sclerosis or another connective tissue disease
assessment of Raynaud’s with puffy fingers, skin thickening or fingertip changes
interpretation of ANA, ENA and systemic sclerosis-related antibodies
advice about appropriate organ screening and monitoring
review of treatment options for Raynaud’s, skin, lung or inflammatory symptoms
coordination with other specialists where needed
a second opinion after previous investigations
Dr Singh’s approach focuses on understanding the full clinical pattern, identifying features that may suggest systemic sclerosis, arranging targeted investigations and developing a personalised plan for monitoring, treatment or onward specialist input.
The aim is to provide clarity, reassurance where appropriate and coordinated care for patients with suspected or established systemic sclerosis.
Why See Dr Singh Privately?
Consultant Rheumatologist and General Internal Medicine Physician at the Royal Free Hospital
Clinical Lead for Rheumatology at the Royal Free Hospital
Works in a Royal Free rheumatology environment where large numbers of patients with systemic sclerosis, Raynaud’s phenomenon and connective tissue disease are cared for
Experience assessing suspected systemic sclerosis, Raynaud’s phenomenon, skin thickening, puffy fingers and digital ulcers
Experience interpreting ANA, ENA and systemic sclerosis-related antibodies in clinical context
Experience assessing multisystem symptoms involving the skin, circulation, joints, lungs, digestive system and kidneys
Works with specialist colleagues in respiratory medicine, cardiology, renal medicine, dermatology and gastroenterology where multidisciplinary input is needed
Experience developing personalised monitoring and treatment plans for complex connective tissue disease presentations
Highly rated by patients on Doctify and Google, with more than 800 patient reviews
Consultant-Led Systemic Sclerosis and Connective Tissue Disease Assessment Across London
Dr Singh offers private assessment for patients with suspected systemic sclerosis, scleroderma, Raynaud’s phenomenon, abnormal autoimmune blood tests and symptoms that may suggest connective tissue disease.
Appointments are available for patients with:
suspected systemic sclerosis or scleroderma
Raynaud’s phenomenon with concerning features
puffy fingers, skin thickening or fingertip changes
fingertip ulcers, pitting or slow-healing sores
positive ANA, ENA or systemic sclerosis-related antibodies
reflux, swallowing symptoms, breathlessness or cough alongside autoimmune features
uncertainty about diagnosis, monitoring or treatment options
requests for a second opinion
Self-pay and insured patients are welcome. Self-pay patients can book directly without a GP referral, while insured patients should check their policy requirements before booking.
Private Systemic Sclerosis / Scleroderma Appointments in London
Private systemic sclerosis and connective tissue disease assessments in Central London, near Harley Street, Marylebone and Oxford Circus.
This clinic may be suitable for patients seeking a central London location or those travelling from outside London.
Private systemic sclerosis and connective tissue disease appointments at the Royal Free Hospital in Hampstead.
This provides access to a major tertiary rheumatology environment where large numbers of patients with systemic sclerosis, Raynaud’s phenomenon and connective tissue disease are assessed.
Private systemic sclerosis and connective tissue disease appointments in West London, convenient for Chiswick, Richmond, Ealing, Acton, Hammersmith and surrounding areas.

Common Questions About Systemic Sclerosis / Scleroderma
These answers cover common questions patients ask when seeking specialist assessment for suspected systemic sclerosis, scleroderma, Raynaud’s phenomenon, abnormal autoimmune blood tests or connective tissue disease symptoms.
-
Systemic sclerosis is an autoimmune connective tissue disease.
It can affect the skin, circulation, joints, tendons and internal organs. The condition varies significantly between patients, so assessment and monitoring need to be individualised.
-
The terms are closely related.
“Scleroderma” means hard skin and is often used by patients and clinicians.
“Systemic sclerosis” is the more precise medical term when the condition may affect the wider body, including the circulation, lungs, digestive system, heart or kidneys.
-
Raynaud’s phenomenon is often one of the earliest symptoms.
Other early features may include:
puffy fingers
skin tightness or thickening
fingertip sores or pitting
reflux or swallowing symptoms
joint or tendon symptoms
abnormal autoimmune blood tests
Not everyone with these symptoms has systemic sclerosis, but specialist assessment can help clarify the pattern.
-
No.
Most people with Raynaud’s do not have systemic sclerosis.
However, Raynaud’s may need further assessment if it starts in adulthood, is severe, causes fingertip ulcers or occurs with puffy fingers, skin thickening, abnormal blood tests or other systemic symptoms.
-
Blood tests may include:
ANA
ENA antibodies
systemic sclerosis-related antibodies
inflammatory markers
full blood count
kidney function
urine testing where appropriate
Blood tests are interpreted alongside symptoms and examination findings. They do not provide the full answer on their own.
-
Some antibody patterns may be associated with systemic sclerosis or related connective tissue diseases.
These may include antibodies such as anticentromere, anti-Scl-70 and anti-RNA polymerase III, among others.
The significance of these antibodies depends on the overall clinical picture, symptoms, examination findings and monitoring needs.
-
Nailfold capillaroscopy is an assessment of the small blood vessels near the fingernails.
It can help identify patterns that may be seen in systemic sclerosis and some other connective tissue diseases.
Not everyone needs this test, but it can be helpful in selected patients with Raynaud’s or suspected systemic sclerosis.
-
Yes.
Systemic sclerosis can sometimes affect the lungs, including inflammation or scarring known as interstitial lung disease, or changes in the blood vessels of the lungs.
Monitoring may include lung function tests, chest imaging and assessment by respiratory specialists where appropriate.
-
Yes, in some patients.
Assessment may include review of symptoms such as breathlessness, palpitations or reduced exercise tolerance, and tests such as echocardiography where appropriate.
-
Yes, although kidney involvement is not present in every patient.
Blood pressure monitoring, kidney function testing and urine assessment may be part of monitoring where appropriate.
-
Yes.
Systemic sclerosis can affect the digestive system and may cause symptoms such as reflux, heartburn, difficulty swallowing, bloating or altered bowel habit.
These symptoms can often be managed, but persistent or troublesome symptoms should be assessed.
-
Yes.
Treatment depends on the features present.
Some patients need treatment for Raynaud’s, reflux, skin symptoms or joint symptoms. Others may need monitoring or treatment for lung, vascular or other organ involvement.
Treatment is personalised according to the pattern and severity of disease.
-
Treatment may include symptom-directed measures, monitoring and specialist medication where appropriate.
Depending on the clinical pattern, treatments may include:
medicines for Raynaud’s such as nifedipine, amlodipine, sildenafil, tadalafil or iloprost
reflux medication
skin, joint or tendon symptom management
immunosuppressive treatments such as methotrexate or mycophenolate in selected patients
biologic or specialist treatments such as rituximab or tocilizumab in selected situations
antifibrotic treatment such as nintedanib in selected patients with lung involvement
Treatment decisions depend on the individual disease pattern, organ involvement and specialist assessment.
-
Yes.
Systemic sclerosis varies widely.
Some patients have mainly Raynaud’s and limited skin involvement, while others may need closer monitoring for internal organ complications.
The aim of assessment is to understand the individual pattern and level of risk.
-
Monitoring depends on the clinical situation.
It may include review of:
Raynaud’s and skin symptoms
blood pressure
kidney function
urine testing
lung function
heart and lung circulation assessment
reflux or swallowing symptoms
medication safety
Monitoring is tailored to the individual patient.
-
Sometimes.
Systemic sclerosis can involve several organ systems, so care may involve respiratory physicians, cardiologists, renal physicians, dermatologists, gastroenterologists or vascular specialists.
Dr Singh works with specialist colleagues where multidisciplinary input is needed.
-
Yes.
A second opinion may be helpful if:
you are uncertain about the diagnosis
you have abnormal antibodies but unclear symptoms
you have Raynaud’s with concerning features
you are unsure about monitoring or treatment recommendations
you have complex or multisystem symptoms
-
Where available, bring:
previous blood test results
autoimmune antibody results
clinic letters
lung function results
scan reports
echocardiogram results
medication list
photographs of Raynaud’s attacks, fingertip changes or skin changes
a timeline of symptoms
Photographs can be particularly helpful because Raynaud’s, fingertip changes and skin symptoms may not be visible during the appointment.
-
A GP referral is not required for self-pay appointments.
If you are using private medical insurance, please check your insurer’s requirements before booking.
-
Yes. Dr Singh sees insured patients.
Please check your insurer’s requirements before booking and bring any required authorisation details.
-
Useful patient resources include:
Information and support for people affected by systemic sclerosis, scleroderma, Raynaud’s phenomenon and related conditions.
Information about assessment and management of scleroderma/ systemic sclerosis.
General information about systemic sclerosis, scleroderma and autoimmune connective tissue disease.
These resources can help you understand your symptoms and prepare questions for your consultation, but they should not replace personalised medical advice.

Ready to Arrange a Specialist Systemic Sclerosis / Scleroderma Assessment?
If you have Raynaud’s phenomenon, puffy fingers, skin thickening, fingertip sores, abnormal autoimmune blood tests or concern about systemic sclerosis, a specialist rheumatology assessment can help clarify the diagnosis and guide appropriate monitoring or treatment.
Dr Singh provides consultant-led systemic sclerosis and connective tissue disease assessment in London, combining specialist rheumatology expertise with experience in complex autoimmune and multisystem presentations.
Related conditions
Systemic sclerosis can overlap with symptoms seen in other autoimmune rheumatic conditions.
If your symptoms suggest a different or related pattern, these pages may also be helpful.